Pain administration looks stealthily straightforward from the exterior. Give an analgesic, reassess, discharge. In real method, it is one of the most nuanced components of nursing. Patients show up strained with anxiety, complex comorbidities, polypharmacy, and a background that may include opioid dependancy or undertreated discomfort. You handle physiology, legislation, documentation, and human emotion, frequently under time stress. That is the context for PUAEME008, the Australian device of competency that concentrates on delivering pain relief in emergency situation and pre-hospital settings. If you are evaluating pain management courses, aiming for a pain monitoring certificate, or selecting short courses suffering monitoring to hone your side, it pays to recognize what this unit covers and just how to turn it into everyday competence.
What PUAEME008 actually implies in practice
PUAEME008 is typically referred to as "Give pain administration." In numerous services it is a prerequisite to provide certain anesthetics under protocol, particularly breathed in representatives and some parenteral alternatives with standing orders. While specific medicine extents differ by jurisdiction and employer, the core of PUAEME008 offer discomfort administration is less concerning the molecule and even more concerning risk-free, effective systems:
- Assessment that divides pain as a symptom from discomfort as a syndrome. An individual with crushing chest discomfort is not the same as an individual with musculoskeletal strain. Risk triage for warnings: shock, neurovascular compromise, area syndrome, sepsis, head injury with wearing away GCS, and possible drug-seeking habits that can shadow assessment. Analgesic option matched to device, seriousness, comorbidities, and atmosphere. The "right medication" depends upon whether you have oxygen, surveillance, IV access, and the abilities to save the airway. Monitoring and titration to effect, not to habit. Repeat evaluations drive dosage choices and escalation. Documentation that defends your clinical reasoning and satisfies medicolegal standards.
Successful prospects in a PUAEME008 supply pain management program reveal that they can use these principles under stress, not just state them in a classroom.
Where registered nurses encounter PUAEME008
I first finished the system throughout a shift from ward nursing to blended ED-ambulance work in a rural solution. We did not have immediate medical cover after hours. Analgesia decisions had repercussions, and the nearby tertiary hospital rested 90 minutes away along roadways that cold over by midnight. PUAEME008 certified me to provide breathed in methoxyflurane, titrate fentanyl under method, and rise for ketamine with medical examination. That range will differ, however the framework really felt universal.
Nurses satisfy this device in 3 major contexts:
- Pre-hospital or access atmospheres where standing orders require an expertise like PUAEME008 to administer analgesia without a prescriber on-site. Emergency divisions and urgent care centers where nurse-initiated analgesia pathways exist. Remote and country facilities where registered nurses manage discomfort during prolonged transportation intervals.
Even if your setting maintains analgesic administration purely under clinical orders, the assessment, surveillance, and documentation components of the unit boost your technique and minimize scientific risk.
Competencies you should demonstrate
A good discomfort monitoring course that aligns to PUAEME008 will certainly not be a slide show of drug truths. Anticipate to demonstrate four broad expertises:
Clinical assessment. You will certainly be anticipated to use a verified pain scale, yet much more importantly you will certainly show you can determine the most likely pain device from background and test. That means centering pain, mapping radiation, checking neurovascular status, evaluating for warnings, and making a decision when analgesia must wait for life-saving interventions. For example, a hypotensive trauma patient could need blood products prior to anything else.
Analgesia choice and dosing. You will validate why a given person gets a certain agent, at a provided beginning dose, with a stated strategy to titrate. Mixed representatives have synergy and trade-offs. As an example, matching paracetamol and an NSAID decreases opioid needs in many bone and joint injuries, yet NSAIDs are a poor choice for suspected crack with bleeding threat or kidney problems. In a wheezing individual with extreme discomfort, ketamine might be more secure than morphine due to its very little breathing depression.
Monitoring and acceleration. The device expects you to expect healing result and adverse effects, to change dose, to change representatives if required, and to know when to call for back-up. Inhaled analgesia might be sufficient for a disjointed shoulder decrease, but a femoral shaft crack during a lengthy transportation might need IV alternatives and local techniques if available.
Communication and documents. You must have the ability to hand over clearly to paramedics, ED coworkers, or a retrieval team. Excellent paperwork adheres to the chain: evaluation, decision, medication and dosage, reaction, damaging results, and strategy. It is likewise your shield if a situation is reviewed.
Matching training course alternatives to your role
The pain administration courses market is crowded. Names vary, and not every offering lines up with PUAEME008. When evaluating carriers of pain monitoring training courses, search for these features:
- Nationally acknowledged unit mapping that specifically notes PUAEME008 supply pain administration, not simply a generic "acute pain" module. Practical circumstances and simulation with abilities sign-off, not only e-learning. If your role includes breathed in analgesia or IV titration, you ought to take care of devices and execute mock dosing and monitoring. Clear evaluation timespan and re-certification needs. Analgesia competencies normally end after 1 to 3 years, with updates on methods and pharmacovigilance. Trainer credentials with pre-hospital or ED experience. You desire instructors who have made these decisions at 3 a.m., not just in lecture halls.
Short training courses suffering monitoring can be beneficial if they enhance the core skills with hands-on technique. A certification training course suffering management that consists of study, pharmacology refresher courses, and emergency discomfort monitoring drills tends to have the best transfer to the floor.
What "good" method resembles at the bedside
A new grad as soon as asked why I spent 3 added mins collecting background prior to offering an analgesic to a person with ankle pain. The reason was simple. The ankle joint was not the trouble. The proximal fibula was tender, the foot was cool, and the individual had pain out of proportion to touch. The differential included a vascular issue, and immediate imaging surpassed early NSAIDs. A pain management certificate ought to show you to adjust this type of judgment.
When analgesia is proper, match the drug to the work:
- Mild to moderate bone and joint pain without warnings typically reacts to paracetamol and an NSAID, plus ice, elevation, and immobilisation. Opioids include little benefit when the basic actions are neglected. Severe stressful discomfort on scene might require inhaled analgesia as a bridge. It gets time to develop IV accessibility, splint properly, and strategy clear-cut analgesia en route. Renal colic can prefer ketorolac when kidney feature permits, with wise opioid titration if needed. Metoclopramide covers nausea or vomiting and can assist with opioid sparing. Fracture reduction or dislocation requires planning: ample analgesia and muscular tissue leisure, monitoring, and post-procedure neurovascular reassessment.
Nurses with PUAEME008 competency are usually the first to act. The very best ones do not skip the fundamentals of convenience: repositioning, cozy coverings, peaceful atmosphere. Those information lower total analgesic needs, especially in older adults.
Pharmacology you will really use
A pain administration accreditation training course hangs around on pharmacology, yet remembering medication graphes is not the result. You need fluency with the patterns.
Paracetamol remains the safest first step in many patients. Dosage issues. Grownups typically receive 1 g by mouth or IV every 6 hours, conscious of advancing everyday limits, liver condition, and poor nutrition. It is stackable with virtually whatever else.
NSAIDs supply strong relief for inflammatory discomfort: strains, renal colic, oral discomfort, and post-op pain when enabled. They are contraindicated or dangerous in GI blood loss, progressed renal problems, poorly controlled heart failure, and late maternity. Programs should cover agent-specific subtleties, like the beginning and renal impact of ketorolac versus ibuprofen, and when to prevent them in trauma with potential bleeding.
Opioids are devices, not services. Morphine, fentanyl, and oxycodone each have accounts that matter. Morphine brings histamine launch and hypotension danger in some patients. Fentanyl works swiftly, which is useful in titration, yet it does not last long. Oxycodone is simple to recommend inadequately and easy to taper poorly. Respiratory depression is the hazard that obtains the headlines, yet the more usual troubles are nausea, vomiting, bowel irregularity, and ecstasy in older grownups. PUAEME008 training emphasizes titrate-to-effect dosing and extensive monitoring.
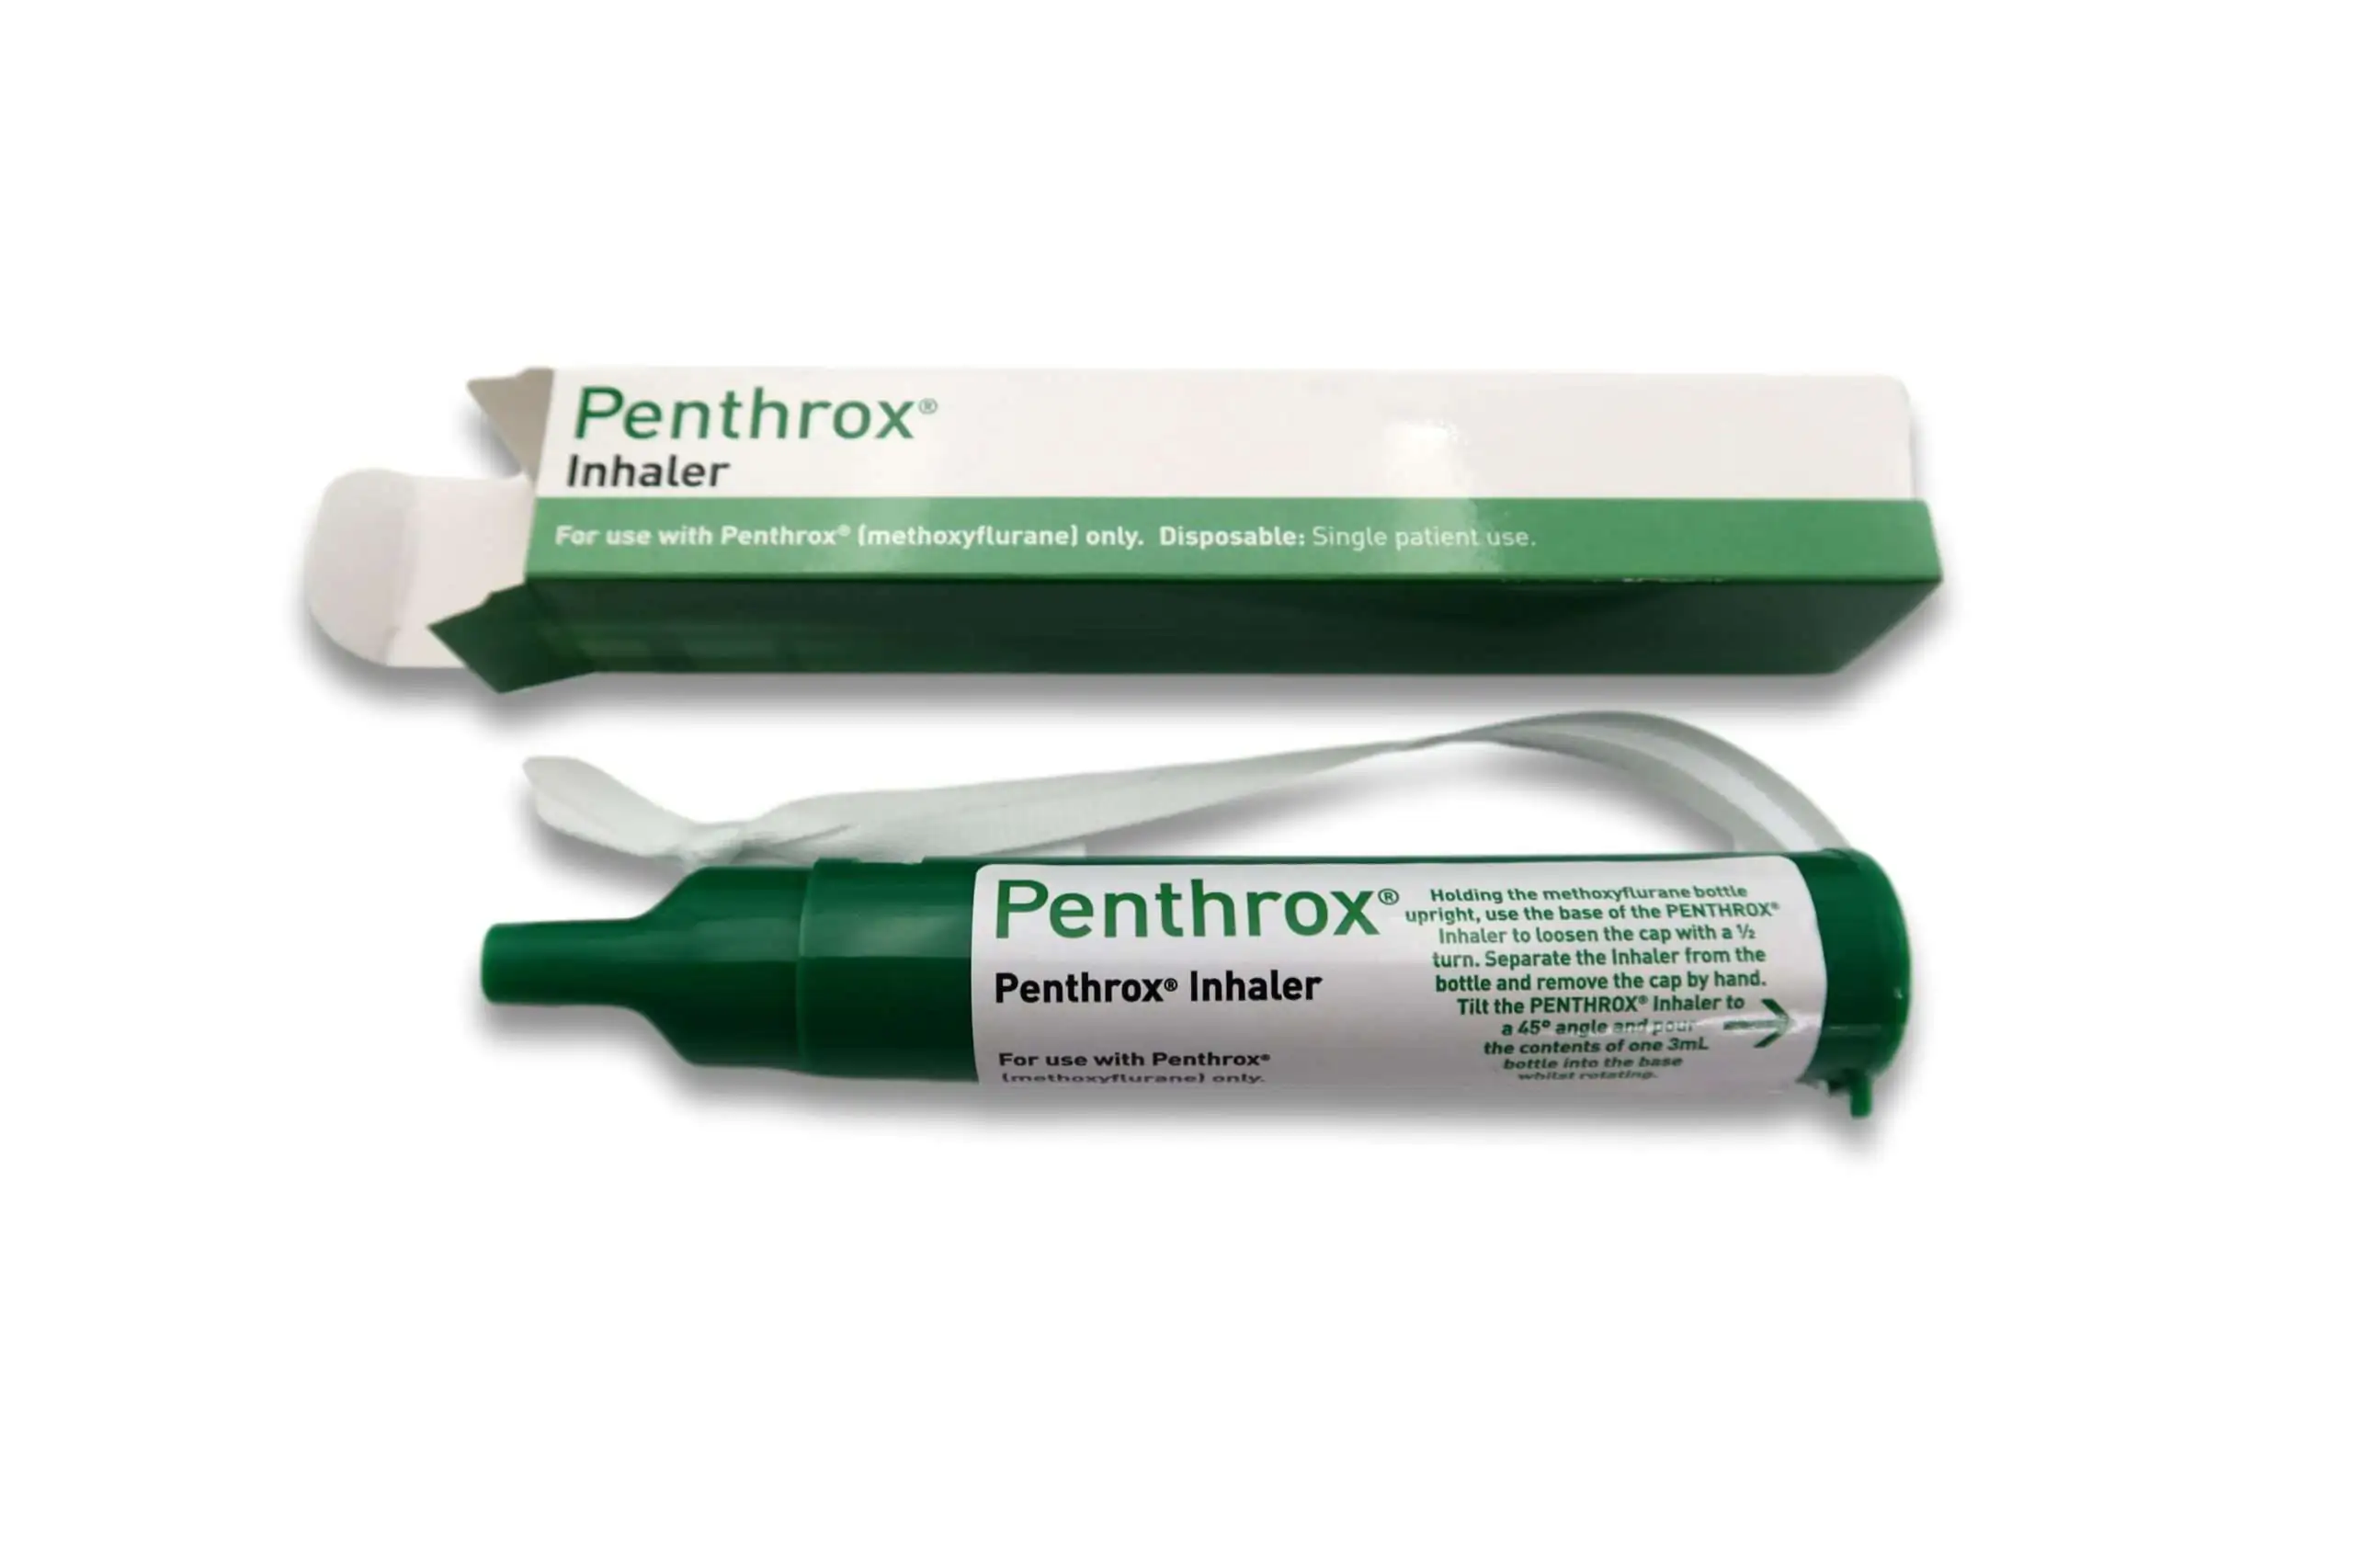
Inhaled analgesia such as methoxyflurane is common in pre-hospital and small procedure setups. It is patient-controlled and fast to begin, though restricted by advancing dose ceilings and prospective nephrotoxicity with extended or repeated usage. You need to recognize exactly how to instruct individuals, ensure adequate air flow puaeme008 provide pain management in restricted spaces, and acknowledge when the inhaler masks hypoventilation or hypoxia.
Ketamine has actually carved out a specific niche in emergency situation discomfort monitoring for extreme injury, burns, and opioid-tolerant people. Sub-dissociative dosing gives analgesia with very little respiratory system clinical depression, however hypertension, tachycardia, and emergence reactions can happen. It requires monitoring and training, which several discomfort monitoring training courses currently include.
Regional blocks are progressively component of nurse-led procedures in some solutions, particularly femoral nerve obstructs for hip fractures monitored by advanced practitioners or doctors. If your scope includes this, your certification training course suffering monitoring must cover sterile strategy, composition, safety and security checks, and documentation.
Adjuvants such as antiemetics, antispasmodics, and neuropathic agents are the difference in between chasing discomfort and controlling it. Small details aid. A very early dosage of ondansetron frequently prevents the cycle of vomit, missed out on analgesic, raised pain, and even more opioid need.
Safety nets and side cases
Two populaces will evaluate your training: older grownups and those with substance usage disorders.
Older adults have reduced physiologic gets and several medicines. Kidney feature may be minimal also if creatinine looks normal. Beginning with non-pharmacologic actions and paracetamol if ideal, avoid long-acting opioids, and screen for ecstasy. I have watched a neighbor's hip fracture client drift into confusion after what appeared like a conventional opioid dose. The resolution was time, liquids, family existence, and a cautious switch to scheduled non-opioid analgesics.
Patients with opioid resistance or a background of misuse require clear, thoughtful treatment. Do not merge under-treated pain with drug-seeking habits. Validate history, make use of objective findings, and communicate a strategy. Short-acting, titratable opioids with close surveillance are usually more secure than high preliminary dosages or long-acting formulas. Involve dependency medicine early if offered. Your documents must reflect assessment, rationale, and agreements made.
Other side situations include pregnancy, where NSAIDs are frequently limited in the third trimester, and the use of nitrous or methoxyflurane calls for obstetric input. Asthmatics may not tolerate certain NSAIDs. Head injuries be entitled to unique care with sedating anesthetics that cloud neuro checks. PUAEME008 training should trigger you to consider these dangers before you prepare a syringe.
How programs assess skills, not simply knowledge
Most pain monitoring programs for nurses that map to PUAEME008 utilize a mixed layout. Anticipate pre-reading on pharmacology, multiple-choice expertise checks, and, crucially, scenario-based assessments. You could handle a simulated substance crack on a manikin, guide a standardized person via breathed in analgesia, or run a situation of serious stomach discomfort with developing vitals. Assessors watch your sequencing, interaction, and paperwork. Time pressure is part of the layout. That is suitable, since the system targets emergency situation discomfort management.
A fair course additionally consists of debriefs that contrast various risk-free approaches. For instance, one candidate might pick fentanyl titration after inhaled analgesia, an additional might prioritize a regional block if a clinician exists to sustain it. Both can be proper if the reasoning and tracking are audio. Excellent facilitators do not show "one ideal means," they educate a collection of risk-free options matched to context.
Documenting pain like a professional
If a situation goes to examine or coronial evaluation, the quality of your discomfort documentation will certainly be on display. Right here is a succinct pattern that has actually stood more than years in ED and pre-hospital setups:
- Record the standard discomfort rating with context: location, personality, radiation, triggers, and feature. "Pain 8/10, sharp, appropriate flank to groin, colicky, worse with movement, nausea or vomiting present." Justify your strategy in one sentence. "Provided most likely kidney colic, begin ketorolac if kidney feature enables, plus ondansetron, reassess 10 minutes, take into consideration fentanyl titration." Document the medication, dose, path, time, and simultaneous treatments like splinting or ice. Reassess at specified intervals. Tape both subjective discomfort ratings and unbiased indications: face, guarding, heart price, respiratory system price, and functional examinations like capability to deep breathe or move the limb. Note unfavorable impacts or absences thereof, any type of dosage modifications, and the handover or discharge strategy, consisting of warnings about driving, added doses, and red flags.
Your notes belong to your pain monitoring accreditation at work. They reveal professional maturity and protect you and your patient.
Choosing between general and role-specific training
There is value in both broad pain administration training and focused, role-specific courses. A general pain monitoring certification program constructs pharmacology and analysis skills that translate throughout setups: ED, wards, aged treatment, and community. Role-specific PUAEME008 supply pain administration programs concentrate on emergency protocols, standing orders, and the logistics of analgesia in less regulated environments.
If you split your time in between ED triage and ambulance support, take the role-specific course first. If you are early in your profession or returning from a leave, begin with a more comprehensive discomfort monitoring certification training course to rejuvenate fundamentals, after that add PUAEME008 for scope.
Pain monitoring courses for physio therapists additionally exist, usually emphasizing non-pharmacologic methods, placing, and graded direct exposure for chronic pain. Interdisciplinary sessions where nurses and physio therapists educate together can be eye-opening. You see exactly how language and movement can lower pain ratings without a single milligram of medication.
Common mistakes and exactly how to prevent them
Three mistakes show up repeatedly in audit conferences. The initial is under-treatment as a result of be afraid of opioids or a lack of confidence. Patients remember when their discomfort is dismissed. If your analysis sustains it, treat early with risk-free agents, monitor closely, and record the plan.
The second is over-reliance on a single drug, particularly opioids. Well balanced analgesia is almost always far better. Matching paracetamol and an NSAID, adding ice or splinting, and utilizing antiemetics minimizes the overall opioid requirement and adverse effects. Assume in combinations.
The 3rd is poor communication. If you titrate analgesia, your colleagues require to understand what you have actually done and how the individual reacted. Handovers that consist of the trajectory of discomfort and feature assist the following group continue safely. "Discomfort from 9 to 6 after 50 mcg fentanyl, able to exist still for CT, respiratory system price steady at 16, plan further 25 to 50 mcg if pain surges over 7, consider ketamine if additional boluses needed."
Turning expertise into habit
Competency is awarded on a date, but ability matures over time. Develop three practices to maintain your PUAEME008 sharp:
- Treat discomfort as a vital indication plus a story. Ask the client what an effective result appears like. For some, it is sleeping without waking; for others, it is strolling to the bathroom. Audit yourself. When a month, review a handful of your situations for time to first analgesia, overall doses, negative effects, and individual comments. Patterns emerge. You will see where you constantly under-dose or overuse an agent. Rehearse the edge instances. If your solution permits it, run tabletop drills: severe burns with minimal IV access, senior hip crack with ecstasy, pediatric fracture with worried moms and dads. Self-confidence expands when you practice outside of crises.
Where PUAEME008 fits within more comprehensive expert growth
A pain administration certification is one called on a ladder. After you understand it, think about expanding right into sedation expertises, injury treatment, or local anesthesia in partnership with medical associates. The web content you find out here likewise boosts chronic discomfort conversations. Clients discover when a nurse discusses why paracetamol and an NSAID, handled routine, will help them relocate physio tomorrow, and just how movement feeds back to decrease discomfort. That is the scientific loophole that reduces readmissions and improves satisfaction.

For managers, sustaining discomfort administration training for registered nurses is a safety and security financial investment. When personnel can evaluate and treat early, time to imaging reduces, treatments go smoothly, and complaints about being neglected decline. A well-structured provide pain monitoring program likewise creates a common language throughout changes and self-controls. You will hear it in handovers.
Final ideas from the floor
I have actually provided analgesia in a well-lit resus bay with full surveillance and in a roadside ditch with rain blowing laterally. The principles did not change. Analyze initially, match medication pain management certificate course to device and risk, titrate with intent, and interact the plan. PUAEME008 formalizes those practices and gives you the legal and specialist scaffolding to act decisively.
If you are considering pain monitoring qualification, choose a supplier that maps cleanly to the unit, presses you in sensible scenarios, and offers practical feedback. If you already hold the credential, keep utilizing it purposely. Discomfort is complicated. Patients remember who took it seriously, and your skill can be the difference between a traumatic memory and a convenient one.